Shadowing-Übung: (English) Acute high grade MCA stenosis PTA and Stenting - Englisch Sprechen Lernen mit Video

Übungsmodus wählen

Jeder Modus öffnet einen Übungsraum im Vollbild.

90 Sätze
Wenn Sätze zu kurz oder zu lang sind, klicke auf Edit, um sie anzupassen.
1
Hello dear colleagues, my name is Almohamed
2
and today we have an acute progressive high -grade stenosis of the left middle cerebral artery
3
which we've treated with PDA and standing.
4
It was a 90 -year -old patient, female, came from home with a phagia, one point on an IHSS scar. As you can see,
5
she has a high -grade stenosis of the M1 segment of
6
the left medocerebral artery with a delay on the time to drain in the CT perfusion.
7
Initially, the patient was treated only with dual antiplatelet therapy with ticagrelor and aspirin.
8
Three days later, the patient has deteriorated and developed a global aphagia with a hemipurrisis,
9
five points on the NIHSS score.
10
And here we have the follow -up.
11
As you can see, she has now a subtotal occlusion of the left medocerebral artery
12
with a severe perfusion deficit in almost all the MCA territory on the left side.
13
So we've performed an acute mechanical regionalization,
14
and here you can see a complete regredience of the middle cerebral artery stenosis and a complete regredience of the perfusion deficit.
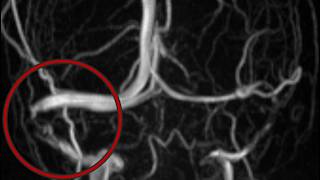
15
And here we have a list of the materials and devices
16
that we've used we've used a PTA Ballon microcatheter NeuroSpeed 2x8 mm
17
and a MicroStand Cradle Heal 3x25 mm with an anti -thrombogenic coating.
18
And here we go.
19
We insert the long sheath NeuronMax with the PenumraSelect catheter into it into the short femoral sheath.
20
and now we're moving the angio table to see the aortic arch.
21
The penumbra select catheter is already configured and now we're trying to navigate the left common carotid artery.
22
Here is it, and now we're pushing the neuromax long sheath a little bit distally,
23
And here we make a road map to see the anatomy,
24
and now we're pushing the preliminary select catheter into the internal cardoid artery and the long sheath NeurMax.
25
We've removed the select catheter because we have reached our first destination, and now we have the intermediate catheter,
26
penumbra 5 max, and now we're inserting the intermediate catheter and trying to navigate the distal parts of the internal carotid artery,
27
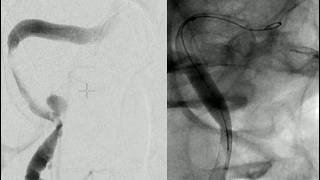
and now we've reached the pituitous segment of the ICA.
28
And here we're preparing our projection on A and B,
29
And as you can see, we have a high -grade stenosis of the left metacerebral artery in the M1 segment,
30
with a very delayed flow in almost the wall MCA territory.
31
And now we need a 3D angiogram so
32
that we can adjust our projection to see the MCA stenosis a little bit better, and make a plan of our treatment.
33
And here we have the 3D angiogram, and as you can see,
34
this is the high -grade MCD stenosis, it's a subtotal occlusion.
35
And now we will use the 3D angiogram to adjust our projections. And here we go.
36
We zoom a little bit and inject contrast medium to see the anatomy.
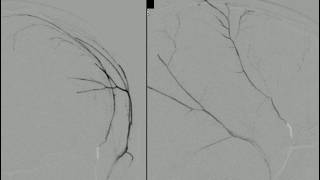
37
And now we can see the stenosis and we will focus on the stenosis.
38
And we will take the maximum zoom that we have, and here is the stenosis on our target acquisition.
39
And now we take these images and make an overlay of that.
40
And here we have the balloon microcatheter NeuroSpeed 2x8 millimeters.
41
And now we are preparing the balloon, inserting contrast medium in the hub of the balloon,
42
and attaching the syringe to the hub applying a negative pressure on the syringe and knocking on it with our finger
43
and now we're attaching the lumen hub of the balloon to saline
44
and we activate the hydrophilic coating by wiping it with a wet sheet and now we're waiting for the microwire Synchro 14,
45
and that's it.
46
And now we insert it in the back of the micro catheter balloon.
47
And here we're shaping the tip of the microwire with the shaper,
48
we just only need a little curve on the tip of the microwire,
49
and now we're inserting the micro -catheter balloon with the micro -wire.
50
And now we are starting navigating the distal parts of the left ICA.
51
Before we navigate the stenosis, we bring the intermediate catheter a little bit distal is so that we have a very good base,
52
and now we are navigating the stenosis, and here we are passing the stenosis,
53
and now we are at the distal parts of the M1 segment and 2 segment of the left MCA,
54
and now we have a stable position of the microwire and here we're pushing the balloon catheter to reach the stenosis.
55
The first distal marker of the balloon catheter is the tip of the micro catheter and the
56
following two markers are the markers of the balloon.
57
And now we have here the inflator.
58
and now we perform the PDA, we go to six bar,
59
and here is the balloon.
60
We deflate the balloon, as you can see we are a little bit distilled in the stenosis,
61
so that we need to pull the balloon a little bit back and re -perform the PDA,
62
so that we make sure that we have reached the stenosis.
63
And now we pull the micro wire And here we have the microstent Credo heel 3 by 25 millimeters.
64
And now we're inserting the microstent in the microcatheter balloon.
65
This is the advantage of this microcatheter balloon.
66
You don't need to change to other microcatheter you just leave it in place and insert the micro stent,
67
and here we have the micro stent.
68
I'm trying to put this tent in the wall segment, M1 segment of the left mediacerebral artery,
69
because it was dysplastic and hypoplastic along the wall M1 segment.
70
And now we're pushing the micro stent a little bit, and pulling the micro catheter balloon backwards,
71
and now we have the stent in place.
72
We can pull the micro stent pusher with the micro catheter balloon.
73
And now we take a round and see our results.
74
And as you can see, complete regredients of the MCA stenosis.
75
The inferior branch of the MCA was already a little bit delayed
76
and we don't want to exaggerate and put another stent in this very small branch.
77
On the left side we have the stenosis before treatment, and on the right side after treatment, and it is a very big difference.
78
And here we have our overview,
79
and as you can see it's a very better blood flow in the MCA territory.
80
And here we have on the left side before the treatment and on the right side after treatment,
81
it is a very big difference and we can see a lot more branches of the MCA territory.
82
And now we've reached the end of our intervention.
83
If you have any questions, please put them in the comments below.
84
You can contact us per email.
85
You can find our email addresses and further contact options in the video description below.
86
Thank you for watching.
87
See you next time.
88
That was Al -Muhammad.
89
Peace out.
90
Thank you.

App herunterladen

Alles, was du zum fließenden Sprechen brauchst

KI-AussprachebewertungJeder Satz bewertet
IPA-TrainingJeden Laut meistern
WortschatzBaue deinen Wortschatz auf
VokabelspielSpielend lernen

Gleicher Kanal

FOR YOU

Empfohlenes Video

Kontext & Hintergrund

Das Video zeigt eine fachliche Präsentation eines medizinischen Eingriffs, in der der Sprecher Schritte zur Behandlung einer akuten Stenose der mittleren Zerebralarterie beschreibt. Die Sprache ist technisch, mit spezifischen medizinischen Begriffen, aber auch mit klaren, strukturierten Sätzen, die sich gut für das Lernen eignen. Solche Videos helfen, nicht nur Fachvokabular zu erweitern, sondern auch die Fähigkeit zu trainieren, komplexe Informationen zu verstehen und nachzuahmen.

Top 5 Phrasen für die tägliche Kommunikation

  • "As you can see" – Ein häufiger Ausdruck, um auf Visuelles hinzuweisen, z. B. in Präsentationen oder Gesprächen: "Wie Sie sehen, hat der Patient eine Verbesserung gezeigt."
  • "We've performed" – Wird verwendet, um ein abgeschlossenes Handeln zu beschreiben: "Wir haben eine Analyse durchgeführt, um die Ursache zu finden."
  • "Now we're preparing" – Gibt einen aktuellen Handlungsstand an: "Jetzt bereiten wir die Materialien für die Besprechung vor."
  • "We need to adjust" – Drückt die Notwendigkeit einer Anpassung aus: "Wir müssen den Plan an die neuen Daten anpassen."
  • "And here we go" – Ein informeller Ausdruck, um einen neuen Schritt einzuleiten: "Und los geht's – lassen Sie uns mit der Aufgabe beginnen."

Schritt-für-Schritt-Shadowing-Anleitung

Um die Englische Aussprache zu verbessern und das Shadowing effektiv zu üben, folgen Sie diesen Schritten: Zuerst hören Sie den Videoausschnitt mehrmals, um die Rhythmik und Intonation zu erkennen. Konzentrieren Sie sich auf kurze Sätze wie "And here we go" oder "Now we're preparing", die sich gut zum Nachsprechen eignen. Nutzen Sie ein Shadowing Site, um die Aufnahmen zu pausieren und nachzuahmen – wiederholen Sie jeden Satz, bis die Aussprache flüssig klingt. Achten Sie auf die Betonung von Wörtern wie "stenosis" oder "perfusion", die in der Medizin häufig vorkommen. Mit Englisch Shadowing trainieren Sie nicht nur die Aussprache, sondern auch das Zuhören und die Reaktionszeit. Ein Tipp: Verwenden Sie die "shadow speech"-Technik, indem Sie den Sprecher direkt nachsprechen, ohne Pause – das stärkt die Sprachfluenz. Englisch lernen mit Videos wie diesem macht Spaß und bringt praxisnahe Ergebnisse. Üben Sie täglich 10–15 Minuten, und Sie werden schnell Fortschritte bemerken!

Grammatik in diesem Video

Die Strukturen, die der Sprecher am häufigsten verwendet, mit den genauen Worten aus dem Video:

StrukturIm Video
Present Perfect have/has + Partizip Perfekt – eine vergangene Handlung, die jetzt noch wichtig istwe've treated · has deteriorated · we've performed
Passiv be + Partizip Perfekt – wichtig ist, was geschieht, nicht wer es tutwas treated · is already configured

Was ist die Shadowing-Technik?

Shadowing ist eine wissenschaftlich fundierte Sprachlerntechnik, die ursprünglich für die professionelle Dolmetscherausbildung entwickelt und durch den Polyglotten Dr. Alexander Arguelles populär gemacht wurde. Die Methode ist einfach aber wirkungsvoll: Du hörst englisches Audio von Muttersprachlern und wiederholst es sofort laut — wie ein Schatten, der dem Sprecher mit nur 1–2 Sekunden Verzögerung folgt. Anders als passives Hören oder Grammatikübungen zwingt Shadowing dein Gehirn und deine Mundmuskulatur, gleichzeitig echte Sprachmuster zu verarbeiten und zu reproduzieren. Studien zeigen, dass es Aussprachegenauigkeit, Intonation, Rhythmus, verbundene Sprache, Hörverständnis und Sprechflüssigkeit signifikant verbessert — was es zu einer der effektivsten Methoden für die IELTS Speaking-Vorbereitung und reale englische Kommunikation macht.

Shadowing-Technik: die vollständige Schritt-für-Schritt-Anleitung lesen →