Shadowing Practice: (English) Acute high grade MCA stenosis PTA and Stenting - Learn English Speaking with Video

Choose a practice mode

Each mode opens a full-screen practice room.

90 sentences
If sentences are too short or too long, click Edit to adjust them.
1
Hello dear colleagues, my name is Almohamed
2
and today we have an acute progressive high -grade stenosis of the left middle cerebral artery
3
which we've treated with PDA and standing.
4
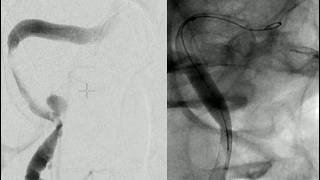
It was a 90 -year -old patient, female, came from home with a phagia, one point on an IHSS scar. As you can see,
5
she has a high -grade stenosis of the M1 segment of
6
the left medocerebral artery with a delay on the time to drain in the CT perfusion.
7
Initially, the patient was treated only with dual antiplatelet therapy with ticagrelor and aspirin.
8
Three days later, the patient has deteriorated and developed a global aphagia with a hemipurrisis,
9
five points on the NIHSS score.
10
And here we have the follow -up.
11
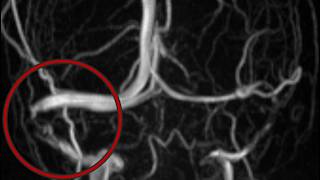
As you can see, she has now a subtotal occlusion of the left medocerebral artery
12
with a severe perfusion deficit in almost all the MCA territory on the left side.
13
So we've performed an acute mechanical regionalization,
14
and here you can see a complete regredience of the middle cerebral artery stenosis and a complete regredience of the perfusion deficit.
15
And here we have a list of the materials and devices
16
that we've used we've used a PTA Ballon microcatheter NeuroSpeed 2x8 mm
17
and a MicroStand Cradle Heal 3x25 mm with an anti -thrombogenic coating.
18
And here we go.
19
We insert the long sheath NeuronMax with the PenumraSelect catheter into it into the short femoral sheath.
20
and now we're moving the angio table to see the aortic arch.
21
The penumbra select catheter is already configured and now we're trying to navigate the left common carotid artery.
22
Here is it, and now we're pushing the neuromax long sheath a little bit distally,
23
And here we make a road map to see the anatomy,
24
and now we're pushing the preliminary select catheter into the internal cardoid artery and the long sheath NeurMax.
25
We've removed the select catheter because we have reached our first destination, and now we have the intermediate catheter,
26
penumbra 5 max, and now we're inserting the intermediate catheter and trying to navigate the distal parts of the internal carotid artery,
27
and now we've reached the pituitous segment of the ICA.
28
And here we're preparing our projection on A and B,
29
And as you can see, we have a high -grade stenosis of the left metacerebral artery in the M1 segment,
30
with a very delayed flow in almost the wall MCA territory.
31
And now we need a 3D angiogram so
32
that we can adjust our projection to see the MCA stenosis a little bit better, and make a plan of our treatment.
33
And here we have the 3D angiogram, and as you can see,
34
this is the high -grade MCD stenosis, it's a subtotal occlusion.
35
And now we will use the 3D angiogram to adjust our projections. And here we go.
36
We zoom a little bit and inject contrast medium to see the anatomy.
37
And now we can see the stenosis and we will focus on the stenosis.
38
And we will take the maximum zoom that we have, and here is the stenosis on our target acquisition.
39
And now we take these images and make an overlay of that.
40
And here we have the balloon microcatheter NeuroSpeed 2x8 millimeters.
41
And now we are preparing the balloon, inserting contrast medium in the hub of the balloon,
42
and attaching the syringe to the hub applying a negative pressure on the syringe and knocking on it with our finger
43
and now we're attaching the lumen hub of the balloon to saline
44
and we activate the hydrophilic coating by wiping it with a wet sheet and now we're waiting for the microwire Synchro 14,
45
and that's it.
46
And now we insert it in the back of the micro catheter balloon.
47
And here we're shaping the tip of the microwire with the shaper,
48
we just only need a little curve on the tip of the microwire,
49
and now we're inserting the micro -catheter balloon with the micro -wire.
50
And now we are starting navigating the distal parts of the left ICA.
51
Before we navigate the stenosis, we bring the intermediate catheter a little bit distal is so that we have a very good base,
52
and now we are navigating the stenosis, and here we are passing the stenosis,
53
and now we are at the distal parts of the M1 segment and 2 segment of the left MCA,
54
and now we have a stable position of the microwire and here we're pushing the balloon catheter to reach the stenosis.
55
The first distal marker of the balloon catheter is the tip of the micro catheter and the
56
following two markers are the markers of the balloon.
57
And now we have here the inflator.
58
and now we perform the PDA, we go to six bar,
59
and here is the balloon.
60
We deflate the balloon, as you can see we are a little bit distilled in the stenosis,
61
so that we need to pull the balloon a little bit back and re -perform the PDA,
62
so that we make sure that we have reached the stenosis.
63
And now we pull the micro wire And here we have the microstent Credo heel 3 by 25 millimeters.
64
And now we're inserting the microstent in the microcatheter balloon.
65
This is the advantage of this microcatheter balloon.
66
You don't need to change to other microcatheter you just leave it in place and insert the micro stent,
67
and here we have the micro stent.
68
I'm trying to put this tent in the wall segment, M1 segment of the left mediacerebral artery,
69
because it was dysplastic and hypoplastic along the wall M1 segment.
70
And now we're pushing the micro stent a little bit, and pulling the micro catheter balloon backwards,
71
and now we have the stent in place.
72
We can pull the micro stent pusher with the micro catheter balloon.
73
And now we take a round and see our results.
74
And as you can see, complete regredients of the MCA stenosis.
75
The inferior branch of the MCA was already a little bit delayed
76
and we don't want to exaggerate and put another stent in this very small branch.
77
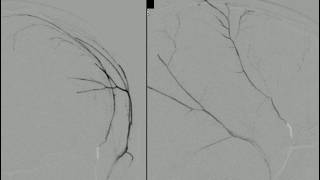
On the left side we have the stenosis before treatment, and on the right side after treatment, and it is a very big difference.
78
And here we have our overview,
79
and as you can see it's a very better blood flow in the MCA territory.
80
And here we have on the left side before the treatment and on the right side after treatment,
81
it is a very big difference and we can see a lot more branches of the MCA territory.
82
And now we've reached the end of our intervention.
83
If you have any questions, please put them in the comments below.
84
You can contact us per email.
85
You can find our email addresses and further contact options in the video description below.
86
Thank you for watching.
87
See you next time.
88
That was Al -Muhammad.
89
Peace out.
90
Thank you.

Download App

Everything you need to speak fluently

AI PronunciationScore every sentence
IPA PracticeMaster every sound
VocabularyBuild your word bank
Vocab GameLearn while playing

Same Channel

FOR YOU

Recommend Video

Why This Video Is Great for Speaking Practice

This video isn’t just about medical procedures—it’s a goldmine for English learners. The dialogue is clear, conversational, and packed with real-world vocabulary, making it perfect for practicing pronunciation and fluency. The speaker’s pace is steady, with natural pauses that mimic everyday speech, so you can easily follow along. Plus, the technical terms are explained in context, which helps you learn new words without feeling overwhelmed. Whether you’re using a shadowing site or a shadowing app, this clip’s structure makes it easy to break down and practice.

Breaking Down Natural Speech

Let’s look at a few lines that sound especially natural. First, “Hello dear colleagues, my name is Almohamed and today we have an acute progressive high-grade stenosis…” The phrase “dear colleagues” is warm and professional, a common way to address a group. Notice how “acute progressive high-grade” flows—each term builds on the last, showing how to connect adjectives smoothly. Next, “As you can see, she has a high-grade stenosis…” “As you can see” is a filler phrase that makes speech sound unscripted, a great example of how to engage listeners. Finally, “We insert the long sheath NeuronMax with the PenumraSelect catheter into it…” The structure here is clear: subject + action + details, which is how most people explain processes. These lines show how to balance clarity with naturalness, a key skill for speaking English well.

A Simple Shadowing Routine for This Clip

Try this shadowing technique to practice: Start by watching the video once to get the gist. Then, play a 5-second segment, pause, and repeat it out loud, mimicking the speaker’s tone and pace. Use a shadowing app to record yourself—this helps you compare your pronunciation to the original. Focus on phrases like “and now we’re moving the angio table” or “we just only need a little curve”—notice how the speaker stresses certain words for emphasis. Do this for 10 minutes a day, and you’ll start to feel more comfortable with natural English rhythm. Over time, you’ll even pick up technical vocabulary that can boost your confidence in professional settings. Remember, the goal isn’t perfection—it’s to sound more like a native speaker, one phrase at a time. Shadowspeaks practice like this can make a big difference in your fluency!

Grammar in this video

The structures the speaker uses most, with the exact words from the video:

StructureIn the video
Present perfect have/has + past participle — a past action that still matters nowwe've treated · has deteriorated · we've performed
Passive voice be + past participle — the focus is on what happens, not who does itwas treated · is already configured

What is the Shadowing Technique?

Shadowing is a science-backed language learning technique originally developed for professional interpreter training and popularized by polyglot Dr. Alexander Arguelles. The method is simple but powerful: you listen to native English audio and immediately repeat it out loud — like a shadow following the speaker with just a 1–2 second delay. Unlike passive listening or grammar drills, shadowing forces your brain and mouth muscles to simultaneously process and reproduce real speech patterns. Research shows it significantly improves pronunciation accuracy, intonation, rhythm, connected speech, listening comprehension, and speaking fluency — making it one of the most effective methods for IELTS Speaking preparation and real-world English communication.

Shadowing technique: read the full step-by-step guide →