Prática de Shadowing: (English) Acute high grade MCA stenosis PTA and Stenting - Aprenda a falar inglês com vídeo

Escolha um modo de prática

Cada modo abre uma sala de prática em tela cheia.

90 frases
Se as frases estiverem muito curtas ou longas, clique em Edit para ajustá-las.
1
Hello dear colleagues, my name is Almohamed
2
and today we have an acute progressive high -grade stenosis of the left middle cerebral artery
3
which we've treated with PDA and standing.
4
It was a 90 -year -old patient, female, came from home with a phagia, one point on an IHSS scar. As you can see,
5
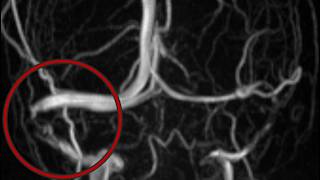
she has a high -grade stenosis of the M1 segment of
6
the left medocerebral artery with a delay on the time to drain in the CT perfusion.
7
Initially, the patient was treated only with dual antiplatelet therapy with ticagrelor and aspirin.
8
Three days later, the patient has deteriorated and developed a global aphagia with a hemipurrisis,
9
five points on the NIHSS score.
10
And here we have the follow -up.
11
As you can see, she has now a subtotal occlusion of the left medocerebral artery
12
with a severe perfusion deficit in almost all the MCA territory on the left side.
13
So we've performed an acute mechanical regionalization,
14
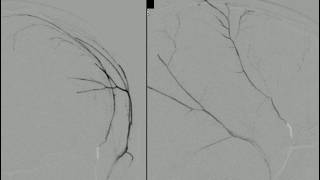
and here you can see a complete regredience of the middle cerebral artery stenosis and a complete regredience of the perfusion deficit.
15
And here we have a list of the materials and devices
16
that we've used we've used a PTA Ballon microcatheter NeuroSpeed 2x8 mm
17
and a MicroStand Cradle Heal 3x25 mm with an anti -thrombogenic coating.
18
And here we go.
19
We insert the long sheath NeuronMax with the PenumraSelect catheter into it into the short femoral sheath.
20
and now we're moving the angio table to see the aortic arch.
21
The penumbra select catheter is already configured and now we're trying to navigate the left common carotid artery.
22
Here is it, and now we're pushing the neuromax long sheath a little bit distally,
23
And here we make a road map to see the anatomy,
24
and now we're pushing the preliminary select catheter into the internal cardoid artery and the long sheath NeurMax.
25
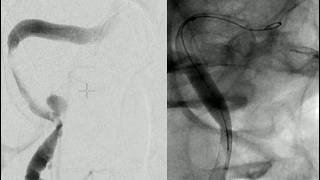
We've removed the select catheter because we have reached our first destination, and now we have the intermediate catheter,
26
penumbra 5 max, and now we're inserting the intermediate catheter and trying to navigate the distal parts of the internal carotid artery,
27
and now we've reached the pituitous segment of the ICA.
28
And here we're preparing our projection on A and B,
29
And as you can see, we have a high -grade stenosis of the left metacerebral artery in the M1 segment,
30
with a very delayed flow in almost the wall MCA territory.
31
And now we need a 3D angiogram so
32
that we can adjust our projection to see the MCA stenosis a little bit better, and make a plan of our treatment.
33
And here we have the 3D angiogram, and as you can see,
34
this is the high -grade MCD stenosis, it's a subtotal occlusion.
35
And now we will use the 3D angiogram to adjust our projections. And here we go.
36
We zoom a little bit and inject contrast medium to see the anatomy.
37
And now we can see the stenosis and we will focus on the stenosis.
38
And we will take the maximum zoom that we have, and here is the stenosis on our target acquisition.
39
And now we take these images and make an overlay of that.
40
And here we have the balloon microcatheter NeuroSpeed 2x8 millimeters.
41
And now we are preparing the balloon, inserting contrast medium in the hub of the balloon,
42
and attaching the syringe to the hub applying a negative pressure on the syringe and knocking on it with our finger
43
and now we're attaching the lumen hub of the balloon to saline
44
and we activate the hydrophilic coating by wiping it with a wet sheet and now we're waiting for the microwire Synchro 14,
45
and that's it.
46
And now we insert it in the back of the micro catheter balloon.
47
And here we're shaping the tip of the microwire with the shaper,
48
we just only need a little curve on the tip of the microwire,
49
and now we're inserting the micro -catheter balloon with the micro -wire.
50
And now we are starting navigating the distal parts of the left ICA.
51
Before we navigate the stenosis, we bring the intermediate catheter a little bit distal is so that we have a very good base,
52
and now we are navigating the stenosis, and here we are passing the stenosis,
53
and now we are at the distal parts of the M1 segment and 2 segment of the left MCA,
54
and now we have a stable position of the microwire and here we're pushing the balloon catheter to reach the stenosis.
55
The first distal marker of the balloon catheter is the tip of the micro catheter and the
56
following two markers are the markers of the balloon.
57
And now we have here the inflator.
58
and now we perform the PDA, we go to six bar,
59
and here is the balloon.
60
We deflate the balloon, as you can see we are a little bit distilled in the stenosis,
61
so that we need to pull the balloon a little bit back and re -perform the PDA,
62
so that we make sure that we have reached the stenosis.
63
And now we pull the micro wire And here we have the microstent Credo heel 3 by 25 millimeters.
64
And now we're inserting the microstent in the microcatheter balloon.
65
This is the advantage of this microcatheter balloon.
66
You don't need to change to other microcatheter you just leave it in place and insert the micro stent,
67
and here we have the micro stent.
68
I'm trying to put this tent in the wall segment, M1 segment of the left mediacerebral artery,
69
because it was dysplastic and hypoplastic along the wall M1 segment.
70
And now we're pushing the micro stent a little bit, and pulling the micro catheter balloon backwards,
71
and now we have the stent in place.
72
We can pull the micro stent pusher with the micro catheter balloon.
73
And now we take a round and see our results.
74
And as you can see, complete regredients of the MCA stenosis.
75
The inferior branch of the MCA was already a little bit delayed
76
and we don't want to exaggerate and put another stent in this very small branch.
77
On the left side we have the stenosis before treatment, and on the right side after treatment, and it is a very big difference.
78
And here we have our overview,
79
and as you can see it's a very better blood flow in the MCA territory.
80
And here we have on the left side before the treatment and on the right side after treatment,
81
it is a very big difference and we can see a lot more branches of the MCA territory.
82
And now we've reached the end of our intervention.
83
If you have any questions, please put them in the comments below.
84
You can contact us per email.
85
You can find our email addresses and further contact options in the video description below.
86
Thank you for watching.
87
See you next time.
88
That was Al -Muhammad.
89
Peace out.
90
Thank you.

Baixar aplicativo

Tudo o que você precisa para falar fluentemente

Pronúncia com IANota em cada frase
Prática de IPADomine cada som
VocabulárioMonte seu banco de palavras
Jogo de vocabulárioAprenda brincando

Mesmo canal

FOR YOU

Vídeo recomendado

Por que praticar a fala com esse vídeo?

Esse vídeo é uma excelente oportunidade para quem quer aprender inglês com vídeos e aprimorar a shadow speak, uma técnica de imitação de fala que melhora fluência e pronúncia. O contexto médico técnico exige clareza e precisão, o que ajuda a treinar a articulação de termos específicos e a estruturação de frases complexas. Ao imitar o narrador, você aprende a falar com confiança em situações que exigem detalhamento, além de expandir seu vocabulário técnico. É um exercício prático para quem quer combinar aprendizado de inglês com compreensão de contextos profissionais.

Gramática e expressões no contexto

O diálogo apresenta estruturas úteis para a shadow speak. 1. Passivo com "was treated": "the patient was treated only with dual antiplatelet therapy" – comum em relatos técnicos para focar no procedimento, não no agente. 2. Expressões de sequência: "Initially... Three days later... And now" – ajudam a organizar a narração temporal, essencial para relatos clínicos. 3. Descrições detalhadas: "a high-grade stenosis of the M1 segment" – uso de adjetivos e termos específicos para caracterizar condições, prático para expandir o vocabulário técnico. 4. Verbos de ação: "we've performed an acute mechanical regionalization" – verbos complexos que exigem pronúncia clara, ideal para treinar a shadowing.

Armadilhas comuns de pronúncia

Algumas palavras no vídeo podem ser desafiadoras para o shadow speak. 1. Stenosis (estenose): a pronúncia /stɪˈnoʊsɪs/ tem um "s" suave no início e um "o" curto, evite pronunciar como "stenósis". 2. Angiogram (angiograma): /ˈændʒiəɡræm/ – a sílaba "an" é curta, e o "g" é suave, não guttural. 3. NeuroSpeed: /ˈnʊroʊspid/ – a junção de "neuro" e "speed" exige fluidez, evite separar as sílabas. 4. Perfusion (perfusão): /pərˈfjuːʒn/ – o "s" no final é quase silencioso, e o "u" tem som longo. Treinar essas palavras no shadowing site ajuda a dominar a pronúncia técnica.

Gramática neste vídeo

As estruturas que o falante mais usa, com as palavras exatas do vídeo:

EstruturaNo vídeo
Present perfect have/has + particípio passado — uma ação passada que ainda importa agorawe've treated · has deteriorated · we've performed
Voz passiva be + particípio passado — o foco está no que acontece, não em quem fazwas treated · is already configured

O que é a Técnica de Shadowing?

Shadowing é uma técnica de aprendizado de idiomas com base científica, originalmente desenvolvida para o treinamento de intérpretes profissionais. O método é simples, mas poderoso: você ouve áudio em inglês nativo e repete imediatamente em voz alta — como uma sombra seguindo o falante com 1-2 segundos de atraso. Pesquisas mostram melhora significativa na precisão da pronúncia, entonação, ritmo, sons conectados, compreensão auditiva e fluência na fala.

Técnica de shadowing: leia o guia completo passo a passo →