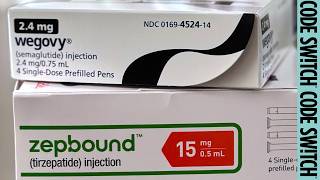
Shadowing Practice: Harvard Thinking: Who should take GLP-1s? - Learn English Speaking with Video

Elige un modo de práctica

Cada modo abre una sala de práctica a pantalla completa.

367 oraciones
Si las oraciones son demasiado cortas o largas, haz clic en Editar para ajustarlas.
1
My real nightmare about GLP -1s is
2
that we end up in a world where we cease to pay attention to the cause of the problem,
3
which is the various reasons that people are struggling with obesity in the first place.
4
It's like in the supermarket aisle, you can go down one aisle in the supermarket
5
and there are other companies selling all these foods that are really bad for us.
6
And then the same companies in the next aisle are selling us the weight loss products
7
that deal with the problem that they caused in the other aisle.
8
GLP -1s have evolved from a treatment of type 2 diabetes into drugs for weight management, leading to a surge in usage,
9
and evidence of promise against a range of other health issues.
10
But given how new these drugs are to the market,
11
medical professionals are only now starting to figure out who should and should not be using them, considering downstream risks like muscle loss,
12
which can particularly impact the elderly.
13
They also raise the question, do we lose anything when we allow taking a pill to become a substitute for lasting lifestyle changes?
14
Welcome to Harvard Thinking, a podcast where the life of the mind meets everyday life.
15
Today, I'm joined by...
16
Caroline Apovian.
17
I am an obesity medicine specialist, professor of medicine at Harvard Medical School.
18
She's also the co -inaugural director of the integrated
19
Mass General Brigham Center for Weight Management and Wellness.
20
Then...
21
Daniel Lieberman.
22
I'm a professor of human evolutionary biology at Harvard University.
23
He's also a best -selling author and recently published
24
Fed Up, What Evolution Reveals About Food, Diet, Health, and Eating Well. And finally...
25
Dr. Fatima Cody -Stanford.
26
I'm an obesity medicine physician -scientist at Mass General Brigham.
27
She's also an associate professor of medicine and pediatrics at Harvard Medical School.
28
And I'm your host, Samantha Leine -Perfos.
29
I'm a writer for the Harvard Gazette.
30
Today, we'll talk about GLP -1s and why we should be excited about their potential and also cautious.
31
And a quick note, Caroline Apovian and Fatima Cody Stanford have worked with pharmaceutical companies, including makers of GLP -1s.
32
Caroline worked as a former consultant and Fatima as a current consultant.
33
Fatima has also received industry funding for her research.
34
What is so magical about this category of drug?
35
The word magical is a very interesting word to use.
36
We call these drugs game changers because of their robust effects on health and in particular on first,
37
you're right, type 2 diabetes and now obesity.
38
And obesity affects 42 % of the United States population.
39
Fatima Cody Stanford was instrumental in getting organizations to distinguish obesity to be a disease and not a matter of willpower.
40
And once that happened, the race was on to develop these drugs for use in obesity.
41
And the reason why they're considered magical is because for the first time in many people's lives,
42
they take a GLP -1 and suddenly, as they say, the food noise is gone.
43
They eat, they're full, they feel like eating healthy food, and they feel like exercising.
44
We never had anything like this before to treat obesity except for metabolic bariatric surgery.
45
So I actually push back a little bit on the terms game changer or magical.
46
I do think that they have definitely created an inflection point in how we think about this disease process.
47
Their potency has changed how the world sees
48
or approaches this disease process due to the fact
49
that we're looking at a total body weight change of either 15 % or 22%, or if we're looking at the triple agonists,
50
you know, getting to closer to 30 % total body weight loss.
51
And so when we look at these,
52
people in the world are beginning to realize that this disease process is beyond this idea of willpower and self -control,
53
that there is actual biology behind this disease.
54
It's not just, oh, eat less and exercise more.
55
And so I think this inflection point of really thinking about this from a disease process,
56
while we can go back to the AMA declaration in 2013 or the World Medical Association, which just happened in 2025,
57
it's when people start to become acclimated to the utilization of these medications and say, wait a minute, I do feel different.
58
Wait a minute, I am making different choices.
59
Wait a minute, these choices are influencing the way I interact with the world around me.
60
That they begin to think, wait a minute, it must be something in the biology of me,
61
and how my biology may differ from those around me.
62
And that was what really got the conversation moving in a different direction, outside of the typical status quo conversation.
63
If I can just add to that from an evolutionary perspective, I want to remind us all that we never evolved to lose weight.
64
We're an interesting species.
65
Human beings have a lot more body fat than most other mammals.
66
Most mammals rarely have more than about 5 % body fat, but in our evolutionary history,
67
we evolved to put on a lot more fat because it's really important for feeding our brains, for our reproductive system, for all kinds of reasons.
68
You know, in the past, it was extremely rare that anybody could gain extra weight, And we never evolved adaptations to lose it.
69
And instead, the key adaptations that we have are hunger and appetite, right?
70
So when we lose weight, we go into what we call negative energy balance.
71
We turn on a whole suite of signaling molecules, hormones, that signal to our brain that we're losing weight and make us hungry.
72
And that's why it's been so hard for so many people for so long to lose weight,
73
because they're fighting against millions of years of really deep and fundamental adaptations.
74
And all of a sudden, for the first time, we've got this drug that can turn off some of those adaptations.
75
From an evolutionary perspective, this is really quite astonishing.
76
The reason why I think these are game changers for the field of obesity medicine is because these are not drugs, right?
77
These are analogs of the hormones that the body makes when you eat food.
78
They have numerous effects on other organs, including the brain.
79
So I'd love to know from you, Dan, what you think about this evolutionary process
80
and using these naturally occurring hormones to then counteract what we've done to the environment.
81
Because it can't be purely genetic because our genes have evolved over millions of years and not over 50 or 100 years.
82
And so what is it about the environment?
83
Is it the ultra processed food?
84
Is it just the fact
85
that we've got all kinds of ways to throw down 3 ,000 calories by rolling down our window at fast food restaurants?
86
Look, everything about our bodies is an interaction between our genes and our environment.
87
Everything, right?
88
And this is no exception.
89
But as you say, our genes haven't changed that much in the last few generations.
90
But in my lifetime, the percentage of Americans with obesity has quadrupled.
91
So obviously it's not because some genes for weight gain have suddenly swept through the population in the last generation or two.
92
But it is true that some people have more proclivity than others.
93
But the other thing is that, of course, there are many factors that affect weight gain.
94
Your microbiome is one of them.
95
Your metabolism.
96
People differ in their metabolic rates.
97
Physical activity has some effect, particularly for weight gain prevention, not so much for weight loss.
98
We could go on for all the various factors, but nobody doubts that the one thing that's changed the most, of course, is our food.
99
When we walk into a supermarket here in Boston, the average supermarket here has 40 ,000 different kinds of food.
100
40 ,000 different kinds of food.
101
And something between 50 and 70, depending upon your definition, are ultra -processed.
102
These are foods where the fiber has been removed, sugar and fat has been added, they've been made hyperpalatable.
103
They've got all kinds of tricks and gimmicks to make us eat more.
104
So there is an association, unquestionably, between the proliferation of processed foods and weight gain.
105
And here's the thing, most of us, once we gain the weight, because of those adaptations, our bodies then reach a new set point.
106
We now call it a settling point because for reasons that I don't think any of us understand,
107
your body fights to put you back at the previous weight, not necessarily your original weight.
108
But then one of the things that I want to bring up, particularly as we think about this from an evolutionary perspective,
109
is I want to think about the group that happens to carry the highest weight, particularly within the U .S population,
110
which happens to be Black women.
111
I want to take us back to our period of enslavement.
112
And if we really look at when Black women started to accumulate great levels of adiposity,
113
it was actually during our periods of enslavement, which is very interesting.
114
Because during the period of enslavement, we didn't have ultra -processed foods.
115
There was high levels of physical activity.
116
But what we don't account for during that timeframe, which really sets us up for the high levels of obesity within this population,
117
the group that I represent, is the allostatic load and stress that started to occur for that population at that time.
118
I think we have to recognize that early predisposition to obesity within the population
119
that carries the highest burden here in the United States now, and when it started for us,
120
and then bring it over to the high burden that then exists, and particularly think about it now in the context of what we see.
121
Yeah.
122
I completely agree.
123
To add to that list, I should have mentioned stress, chronic stress, for example, which is of course a function of socioeconomic status and racism.
124
There are epigenetic effects.
125
So yeah, I 100 % agree with you.
126
This is a multifactorial problem.
127
There's no question that our food supply is a major one, but it's not the only one.
128
One thing about food that I did want to ask about was this idea of food noise.
129
What does that mean?
130
And what is it about GLP -1s that are affecting it?
131
For people that have food noise, they are constantly thinking about food.
132
It doesn't matter if it's ultra processed, it doesn't matter if it's not.
133
They have this constant desire to want to eat.
134
And for those that are responders to GOP -1s, when they go on something like a GOP -1,
135
they say they no longer think about eating in the way that they did before.
136
So that volume that might be really high, you turn that down and they're like, wait a minute, I'm not thinking about food.
137
I actually forgot to eat breakfast, lunch, and wait a minute, it's dinner time.
138
I turned down the volume.
139
So this thinking about food, it's no longer a focal point.
140
For some people, not everyone, GLP -1s also reduce other kinds of noise, other forms of addiction for people who have issues with,
141
say, tobacco or certain pharmaceuticals or alcohol.
142
And so there's something just really quite extraordinary about this hormone and its multiple effects.
143
And because you have to remember that hormones evolved to do multiple things,
144
but I like to think of hormones really as allocators of investment and energy.
145
And this is a hormone that's basically telling the body to turn down stuff.
146
We have hormones that turn things up and hormones that turn things down.
147
It's a very crude simplification.
148
But what's amazing is that GOP1s normally in human beings, they have very short action.
149
And the real turning point for this was
150
that they used essentially the GLP -1 of a lizard that eats only once every three weeks or something.
151
I can't remember the Gila monster.
152
And that has a much longer acting effect than the human version.
153
And now we're finding out all kinds of fascinating things about this hormone.
154
So one thing I want to talk about too is that the usage for these drugs has increased significantly.
155
Secondly, I think as of last year, one in eight American adults was using GLP -1s for weight loss.
156
Dan, you have been vocal about some of your skepticisms with GLP -1s.
157
I would love to hear some of the concerns and or limitations that we are seeing.
158
I'm not skeptical.
159
So I have two concerns really that are overriding.
160
The first is that the evidence is that a lot of people on GLP -1s are losing a lot of muscle mass.
161
As with bariatric surgery, where you have very extreme weight loss, people can lose something like 20, 30, even more percent of their body weight.
162
And a large percentage of that, maybe up to 30 percent of that can be fat -free mass.
163
So we're not talking about body fat.
164
We're talking about other tissues.
165
And some of that's muscle.
166
And one of the big issues for aging in the United States is sarcopenia, which is age -related muscle loss.
167
And so it's not a skepticism, but it's a concern that individuals who are on GLP -1s losing a lot of weight,
168
if they don't include some degree of strength training, they could be at greater risk for age -related muscle loss for sarcopenia.
169
And that's really concerning because that becomes a kind of vicious cycle.
170
Once you get very frail, you become less physically active, you become even less active.
171
I can speak from personal experience with my parents.
172
It's a really challenging thing to watch.
173
My other concern, of course, is that a lot of people, and Caroline and Fatima will know the data better than I,
174
but there's a fairly high quit rate for these drugs.
175
I think the latest study I saw, and I'm sure there's better data now,
176
was that over 50 % of people are quitting it between one and two years.
177
And then the other concern is what happens when they quit, right?
178
Are they gaining weight back?
179
But you guys know more about this than I do.
180
Yeah, these are two big areas, Dan.
181
The muscle loss concept is very much debated.
182
First of all, when you lose any kind of weight by any means, you're right, bariatric surgery, drugs,
183
diet, and exercise, you don't lose just fat, right?
184
Because if you have obesity, there's extra muscle to hold everything together.
185
And the Krebs cycle metabolism, you need amino acids to burn energy.
186
So you can't just lose fat.
187
There is always a certain percent that is muscle.
188
And you really can't go below losing 20, 25 percent of the total as muscle.
189
So that's physiology.
190
Yes, there are people who lose more, 30 or 40 percent.
191
We think it may have to do with the rapidity of the weight loss if they're not eating enough protein.
192
And yes, if they're not doing strength training.
193
But I think that the largest concern about muscle mass should be with the older population.
194
The older population is already losing muscle mass, something like 1 % per year after the age of 40 or 50.
195
And yes, those people on GLP -1s
196
or after bariatric surgery may lose more muscle mass and develop dysfunction and frailty and sarcopenia and also bone loss.
197
So that's a valid concern.
198
And we've already had people in the older population losing 40 pounds on Wagovi
199
and then falling and fracturing their tibfib because it was fragile.
200
I definitely think that the muscle loss piece is by far more germane to those that are older adults, and particularly with the new
201
Medicare Bridge program that's just come into place, right?
202
So for those who are unaware, Medicare has decided to start covering these medications for individuals with obesity as of July 1st,
203
which means that there's going to be a sizable percentage of the population that now have access to these drugs.
204
The program appears to be in place from July 1st of 2026 through December 31st of 2027,
205
We have no idea what's going to happen after that.
206
But a sizable percentage of the population, particularly those that are 65 plus, will gain access.
207
Now, we also know that population has a higher tendency to have issues like sarcopenia.
208
And we do need to think about protein and muscle retention during that population.
209
And so this is what I really like to emphasize with my patients.
210
And this is how I bring them into the conversation, regardless of age.
211
I say in our 20s and 30s, I like to think of a one -to -one ratio of cardio to strength.
212
So 30 minutes of strength for 30 minutes of cardio.
213
When we get into our 40s and 50s where I exist in that middle age range,
214
I think of it as a two to one strength to cardio ratio.
215
So for every 60 minutes of strength, 30 minutes of cardio.
216
In our 60s and 70s, I like to think of a three to one strength to cardio ratio.
217
So for every 90 minutes of strength, we should have 30 minutes of cardio.
218
And if we get into our 80s and 90s, I like to think of it as a four to one strength to cardio ratio.
219
So for every 120 minutes of strength training, 30 minutes of cardio.
220
Now, tell me how many people actually do that.
221
Zero own.
222
Exactly.
223
Unless you're me, right?
224
And so this is what I emphasize with my patients.
225
And when they're getting that mantra, they begin to realize the importance of strength training,
226
because we've been fed this idea that it's cardio, cardio, cardio, cardio, cardio.
227
But if you're really strength training in the way that we're talking about it, you are getting that heart health benefit from doing the strength training.
228
Now, moving into your second piece, which is how people pull back the utilization.
229
So 50 % discontinuation of GOP -1s.
230
The number one reason for the discontinuation is cost, access.
231
But what we've seen, and I will use Massachusetts as a case in point for discontinuation for these medications.
232
Up until January 1st of 2026, Massachusetts had the best utilization and coverage for GOP -1 receptor agonists.
233
If we look at employer -sponsored insurance, here in Massachusetts, the big four are Mass General Brigham,
234
Harvard Pilgrim, Tufts, and Blue Cross Blue Shield of Massachusetts or New England.
235
All of these insurers were covering GOP -1s for patients with overweight and obesity.
236
But as of January 1st, pulled back coverage for this patient population.
237
What happened was our patient populations got pulled off of these medications.
238
Now, for persons that are high -income earners, they were able to retain utilization of these medications.
239
Price point between $300 and $450 a month out -of -pocket price.
240
But if you're a high -income earner, that's not too much for you.
241
If you're not a high -income earner, it's a lot.
242
That's a very important point.
243
I just saw a patient virtually because he weighs 625 pounds.
244
But he did weigh 725 pounds,
245
and he lost 100 pounds getting ready for bariatric surgery with ZepBound.
246
He lost 100 pounds on the top dose of ZepBound.
247
And then in July, it got pulled.
248
He is now gaining weight.
249
And I just messaged the surgeon and said, you better get him to surgery now because he's going to gain that weight back.
250
You got to get him to surgery now.
251
This is the segment of the population, BMI over 60, still rising exponentially in the United States and probably worldwide.
252
So what are we going to do about this weight regain?
253
It's causing a lot of oxidative stress,
254
especially as you gain it rapidly so that food noise comes back very aggressively,
255
especially if you've lost 100 pounds and you suddenly stop the GLP -1, you suddenly think that you're starving to death.
256
My other concern about GLP -1s is about prevention and really goes back to what we started off talking about,
257
which is that, so I have this term I apologize for, which I created, called disevolution.
258
When we treat the symptoms rather than the causes of a mismatched problem.
259
Then we just keep the cycle going.
260
My real nightmare about GOP -1s is
261
that we end up in a world where we cease to pay attention to the cause of the problem,
262
which is the various reasons that people are struggling with obesity in the first place.
263
It's like in the supermarket aisle, you can go down one aisle in the supermarket
264
and there are other companies selling all these foods that are really bad for us.
265
And then the same companies in the next aisle are selling us the weight loss products
266
that deal with the problem that they caused in the other aisle.
267
Ultimately, what we should all really want to do is prevent this problem from happening in the first place.
268
That got to another question that I wanted to ask all of you.
269
It is amazing that these medications are able to so effectively help people.
270
And also, what happens when it becomes a substitute for the lifestyle change that needs to happen?
271
I don't think it's a substitute for the lifestyle changes.
272
So by the time the patients get to us, these patients have tried and failed, or that lifestyle has tried and failed them.
273
They can list 25 to 30 different programs that they've tried and failed.
274
It's like the biggest loser concept.
275
It worked for a short period of time, and then it didn't work, and their bodies came back.
276
And so then they're coming to us because they're like, okay, look, I've tried all these things.
277
And so let's say they go on these medications, and they're like, oh, wait a minute, this works.
278
Now they can actually go work out they are feeling good about themselves going to the gym
279
and seeing the results pay off while they're on the medications.
280
Because as Dan mentioned, if it pulls back, they're regaining.
281
And then they're feeling lack of confidence.
282
Their self -worth and self -esteem unfortunately deteriorates because they're like, here I am.
283
I finally got to the quote unquote promised land and it was snatched from me.
284
I always say nobody wants to have obesity.
285
If diet and exercise worked and they wouldn't be stigmatized walking down the street because they have obesity.
286
They would have done it.
287
We have a disease.
288
GLP -1s are not removing the cause of the problem,
289
but what it is doing is it is reducing the body weight set point.
290
I fully agree with you two, but I do want to ask you about children.
291
So as I'm sure you both know, there are very scary statistics about the percentage of teenagers in the United States who are classified with obesity.
292
It's somewhere between 20 and 30%, depending upon which study you believe in.
293
Should we be giving GLP -1s to those kids?
294
Me, my concern is how do we prevent those kids from getting into that problem in the first place?
295
Okay, so I treat the full age spectrum.
296
My patients go from two to 90 plus.
297
And I think about who are the pediatric patients who actually end up in my clinic.
298
It's usually the children of my patients.
299
So how do I prevent this?
300
If I can get the patients modified preconception, I have a higher likelihood of having children that have a lesser likelihood of obesity.
301
The best study was a study that came out in the Journal of Clinical Endocrinology and Metabolism back in 2009,
302
which demonstrated that children born to mothers
303
that undergone bariatric surgery had a three -fold decrease in likelihood of obesity in the mother after she had undergone surgical intervention.
304
So if we can modify the weight status of the parent's preconception, we can modify the children's weight status.
305
Let's come back to the question you specifically asked.
306
Do we utilize these medications in children and how does that work?
307
I do treat patients as young as 12 with GLP -1 receptor agonists.
308
What I have found in treating these patients, first of all, when I get pediatric patients,
309
I find that they actually have health status that's much worse than my adult patients.
310
Their cholesterol is much worse.
311
Their liver function tests are much worse.
312
Their hemoglobin A1c, which is their blood sugar, is much worse.
313
What I also find when using these medications is
314
that they usually respond much better than my adult patients to the therapy when given to them.
315
That gives them a likelihood of having a much better life
316
moving forward than I did prior to the advent of these medications.
317
So I see these patients go from looking down in my visit, not actually making direct eye contact because their self -esteem,
318
their value, their self -worth is so tied into their weight, to making eye contact, having an improvement of their cardiometabolic health,
319
and allowing them to move forward into adulthood with a better life.
320
When we talk about GLP -1s, obviously they're so new.
321
We're still figuring out so many things.
322
What do you feel we are not talking about enough?
323
or what are things that we really should be focusing on as an area of further research?
324
I think that GLP -1's just created this explosion in social media, and in research, and in the medical community.
325
And I think what we're not talking about adequately enough is who are they for?
326
The protocols are not in yet.
327
We're writing guidelines with the ADA, but we're not categorizing patients.
328
I think the highest risk patients should be getting our more potent drugs and be considered for metabolic surgery.
329
The BMI is not an adequate measure of body fat.
330
We still don't have the right tools to measure who is at risk.
331
And social media now is on a rampage which compounded GLP -1s that people are taking to lose 10 pounds.
332
If you take a GLP -1 to lose 10 pounds, you don't have the disease of obesity.
333
Are you setting yourself up?
334
for stopping the medication, gaining even more weight back, and developing a problem that you didn't have in the first place.
335
So if you're going to take a GLP -1 just to lose 10 pounds so you can look good in your dress,
336
you should not be taking a GLP -1.
337
It's not for you.
338
I think one of the key things that we're not talking about are the potential use case scenarios for GLP -1s.
339
What we do know is we have GLP -1s were initially approved for type 2 diabetes, and then we moved into obesity and obstructive sleep apnea.
340
But we're going to continue to see different use case scenarios for these medications.
341
And there's a variety of research interests
342
that move outside of the space of cardiometabolic health into looking at rheumatologic conditions like gout and rheumatoid arthritis.
343
We're looking at disorders like Alzheimer's disease and Parkinsonism and things of that sort.
344
And so as we begin to see this blossoming of research,
345
I think it's going to be interesting to see just really how these medications begin to explode beyond the cardiometabolic use,
346
and then how the dosing structure will change to accommodate these potential use case scenarios as we move forward.
347
My thing that I really hope we can use GLP Wands to talk more about is
348
that there really are game changers for treatment.
349
There's no question about that.
350
But they're not game changers for prevention.
351
Wouldn't the best world be where you didn't have to use these in the first place?
352
The fact of the matter is we do, and we should, and they are helping a lot of people,
353
and we'll find out better ways to use them and maybe other adjuvants that can help us use them better.
354
But hopefully we can leverage the opportunities that GLP -1s are giving us for treatment to also think more about prevention.
355
Thank you all for joining me for this conversation.
356
My pleasure.
357
Thank you.
358
It's been a pleasure speaking to everyone.
359
Thanks for listening.
360
For a transcript of this episode and our other episodes, visit harvard .edu slash thinking.
361
If you liked this episode, rate and review us on Apple or Spotify, or like us on YouTube.
362
It helps others find us.
363
This episode was hosted and produced by me, Samantha Lainey -Perfos.
364
It was edited by Ryan Mulcahy, Paul Mekishima, and Sarah Lamade.
365
Original music and sound design by Noel Flatt.
366
Produced by Harvard University.
367
Copyright 2026.

Descargar app

Todo lo que necesitas para hablar con fluidez

Pronunciación con IAEvalúa cada oración
Práctica de IPADomina cada sonido
VocabularioConstruye tu banco de palabras
Juego de vocabularioAprende mientras juegas

Mismo canal

FOR YOU

Recomendar Video

Vocabulario y notas de pronunciación para esta lección

Esta lección de conversación se basa en el vídeo “Harvard Thinking: Who should take GLP-1s?”. Las palabras que más se repiten: Glp, weight, obesity, patient. Este vídeo tiene 252 frases y 4750 palabras para practicar shadowing. La parte hablada dura 27:36. El hablante habla a un ritmo natural de unas 172 palabras por minuto, cercano a una conversación cotidiana. El 83 % de las palabras está entre las 3.000 más comunes del inglés; conviene repasar el resto antes de empezar.

Vocabulario clave de este vídeo

15 palabras del vídeo que vale la pena aprender, con su pronunciación y significado:

PalabraPronunciaciónSignificado
obesity sustantivo/ə(ʊ)ˈbiːsɪti/obesidad, sobrepeso
muscle sustantivo/ˈmʌs.əl/músculo
medication sustantivo/mɛdɪˈkeɪʃən/medicamento, medicación
hormone sustantivo/ˈhoɹmoʊn/hormona
aisle sustantivo/aɪ̯l/nave
evolutionary adjetivo/ˌiː.vəˈluː.ʃən.ɛɹ.i/evolutivo, evolucionista
evolve verbo/ɪˈvɑlv/desarrollar
supermarket sustantivo/ˌsupɚˈmɑɹkət/supermercado
percentage sustantivo/pə(ɹ)ˈsɛntɪd͡ʒ/porcentaje
adaptation sustantivo/ˌæd.æpˈteɪ.ʃən/adaptación
ratio sustantivo/ˈɹeɪ.ʃoʊ/razón, cociente
gene sustantivo/d͡ʒiːn/gen, gene
lifestyle sustantivo/ˈlaɪfˌstaɪl/género/estilo de vida/vivir/vivencia, estilo/género vital/vivencial
prevention sustantivo/pɹɪˈvɛnʃən/prevención
biology sustantivo/baɪˈɑ.lə.d͡ʒi/biología

Phrasal verbs que vas a escuchar

PalabraSignificado
figure out verboaveriguar, captar
find out verboaveriguar, anoticiarse
move forward verboir adelante, adelantar
turn down verborechazar
bring up verbolevantar, alzar
pay off verbovaler la pena, salir a cuenta
turn off verboapagar

Gramática en este vídeo

Las estructuras que más usa el hablante, con las palabras exactas del vídeo:

EstructuraEn el vídeo
Present perfect have/has + participio pasado — una acción pasada que sigue importando ahorahave evolved · have worked · has also received
Voz pasiva be + participio pasado — importa lo que ocurre, no quién lo hacehas been removed · we've been fed · is cost
Oraciones de relativo who / which + oración — información extra sobre una persona o cosaenslavement, which is · example, which is · people who have

Pronunciación a tener en cuenta

El hablante usa 82 contracciones y formas reducidas, como they're, we're, I'm. Dilas en su forma corta, tal como las oyes.

  • Los sonidos de “sh” y “zh”: medication /mɛdɪˈkeɪʃən/, evolutionary /ˌiː.vəˈluː.ʃən.ɛɹ.i/, adaptation /ˌæd.æpˈteɪ.ʃən/, ratio /ˈɹeɪ.ʃoʊ/, prevention /pɹɪˈvɛnʃən/
  • Palabras largas — cuida el acento: obesity /ə(ʊ)ˈbiːsɪti/, medication /mɛdɪˈkeɪʃən/, evolutionary /ˌiː.vəˈluː.ʃən.ɛɹ.i/, supermarket /ˌsupɚˈmɑɹkət/, adaptation /ˌæd.æpˈteɪ.ʃən/

Sonidos difíciles para hispanohablantes:

  • s + consonante al inicio — sin añadir una “e” delante: scary /ˈskɛə.ɹi/, specialist /ˈspɛʃəlɪst/, spectrum /ˈspɛktɹəm/, suite /swiːt/, sponsor /ˈspɒn.səː/
  • /v/ — no es /b/: los dientes tocan el labio inferior: evolutionary /ˌiː.vəˈluː.ʃən.ɛɹ.i/, evolve /ɪˈvɑlv/, prevention /pɹɪˈvɛnʃən/, everyday /ˈɛvɹiˌdeɪ/, valid /ˈvælɪd/
  • /z/ — sonora, no /s/: diabetes /ˌdaɪəˈbiːtiːz/, metabolism /məˈtæb.əˌlɪz.əm/, physically /ˈfɪz.ɪ.kli/, emphasize /ˈɛm.fə.saɪz/, racism /ˈɹeɪsɪzm̩/

Cómo practicar con este vídeo

  1. Escucha el vídeo entero una vez sin hablar y anota las palabras que no conoces.
  2. Empieza a velocidad 0,75×, haz shadowing frase por frase y vuelve a la velocidad normal cuando te resulte fácil.
  3. Grábate y compara con el original, prestando atención a palabras como obesity, muscle, medication.

¿Qué es la Técnica de Shadowing?

Shadowing es una técnica de aprendizaje de idiomas respaldada por la ciencia, desarrollada originalmente para la formación de intérpretes profesionales y popularizada por el políglota Dr. Alexander Arguelles. El método es simple pero poderoso: escuchas audio en inglés nativo y lo repites en voz alta de inmediato, como una sombra que sigue al hablante con solo 1-2 segundos de retraso. A diferencia de la escucha pasiva o los ejercicios de gramática, el shadowing obliga a tu cerebro y músculos de la boca a procesar y reproducir simultáneamente patrones de habla reales. Las investigaciones muestran que mejora significativamente la precisión de la pronunciación, la entonación, el ritmo, el habla conectada, la comprensión auditiva y la fluidez al hablar, convirtiéndola en una de las metodologías más efectivas para la preparación del IELTS Speaking y la comunicación en inglés en el mundo real.

Técnica de shadowing: lee la guía completa paso a paso →